Brand: Kadcyla|Also known as T-DM1
Initial US Approval
- 20131
Indications
- As a single agent for the treatment of patients with HER2-positive metastatic breast cancer who previously received trastuzumab and a taxane, separately or in combination. Patients should have either received prior therapy for metastatic disease, or developed disease recurrence during or within six months of completing adjuvant therapy.1,2
- As a single agent for the adjuvant treatment of patients with HER2-positive early breast cancer who have residual invasive disease after neoadjuvant taxane and trastuzumab-based treatment.1,3
Recommended Dose/Route
- 3.6 mg/kg by intravenous infusion every 3 weeks (21-day cycle) until disease progression or unacceptable toxicity in the metastatic setting, or for a total of 14 cycles in the adjuvant setting unless there is disease recurrence or unacceptable toxicity.1
- First infusion over 90 minutes; subsequent infusions over 30 minutes if prior infusions were well tolerated. Do not administer at doses greater than 3.6 mg/kg.1
- Do not substitute KADCYLA for or with trastuzumab or fam-trastuzumab deruxtecan. Name confusion among the three trastuzumab-based products is a recognized medication-error risk.1
- Assess transaminases and bilirubin before each dose and left ventricular ejection fraction before initiation and every 3 months during treatment.1
Dose Reductions for Adverse Reactions
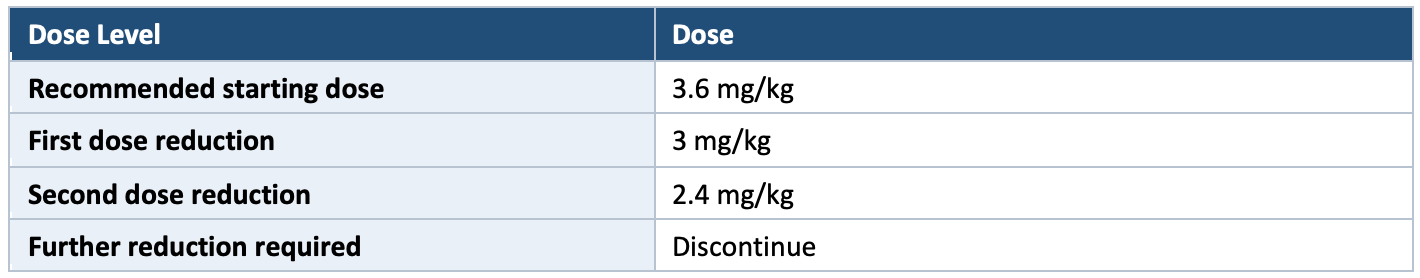
- Do not re-escalate the dose after a reduction has been made.1
Pivotal Study
EMILIA (NCT00829166) and KATHERINE (NCT01772472)
- EMILIA key inclusion criteria: HER2-positive metastatic breast cancer previously treated with trastuzumab and a taxane; 991 patients randomized to ado-trastuzumab emtansine or lapatinib plus capecitabine. Median duration of study treatment was 7.6 months in the KADCYLA group.1,2
- KATHERINE key inclusion criteria: HER2-positive early breast cancer with residual invasive disease in the breast or axillary nodes after neoadjuvant taxane and trastuzumab-based therapy; randomized to 14 cycles of ado-trastuzumab emtansine or trastuzumab.1,3
Efficacy
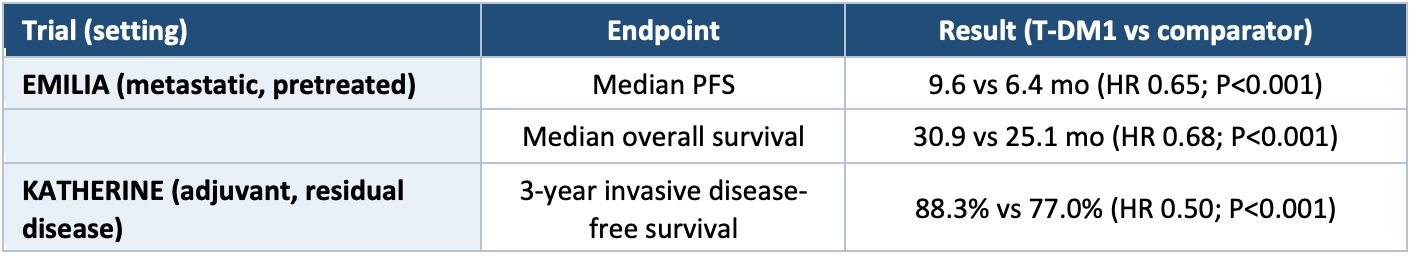
- KATHERINE established post-neoadjuvant escalation for patients with residual disease and is the basis for the adjuvant indication. Residual invasive disease after neoadjuvant HER2-directed therapy identifies a higher-risk group in whom switching agents, rather than continuing trastuzumab, improves outcomes.1,3
Safety
- Common adverse reactions (>25%), EMILIA: fatigue, nausea, musculoskeletal pain, hemorrhage, thrombocytopenia, headache, increased transaminases, constipation, and epistaxis.1
- Common adverse reactions (>25%), KATHERINE: fatigue, nausea, increased transaminases, musculoskeletal pain, hemorrhage, thrombocytopenia, headache, peripheral neuropathy, and arthralgia.1
- Key warnings: hepatotoxicity, cardiac toxicity, and embryo-fetal toxicity in the boxed warning; plus pulmonary toxicity including interstitial lung disease, infusion-related reactions and hypersensitivity, thrombocytopenia, peripheral neuropathy, and neurotoxicity.1
- Thrombocytopenia: overall incidence 31% in EMILIA (Grade 3 or higher 15%) and 29% in KATHERINE (Grade 3 or higher 6%). Incidence and severity are higher in Asian patients, in whom Grade 3 or higher rates were 45% in EMILIA and 19% in KATHERINE. Monitor platelet counts before initiation and before each dose.1
- Peripheral neuropathy: overall incidence 32% in KATHERINE versus 17% with trastuzumab. In EMILIA, Grade 3 or higher peripheral neuropathy occurred in 2.2%.1
- In EMILIA, 7% of patients discontinued KADCYLA due to an adverse reaction and 16% had adverse reactions leading to dose reduction, most frequently thrombocytopenia and increased transaminases. Grade 3 or higher adverse reactions occurred in 43% of the KADCYLA group versus 59% with lapatinib plus capecitabine.1
References
1. KADCYLA (ado-trastuzumab emtansine) for injection. Prescribing information. Genentech, Inc. Accessed August 2026.
2. Verma S, Miles D, Gianni L, et al. Trastuzumab emtansine for HER2-positive advanced breast cancer (EMILIA). N Engl J Med. 2012;367(19):1783-1791. doi:10.1056/NEJMoa1209124
3. von Minckwitz G, Huang CS, Mano MS, et al. Trastuzumab emtansine for residual invasive HER2-positive breast cancer (KATHERINE). N Engl J Med. 2019;380(7):617-628. doi:10.1056/NEJMoa1814017